Cart
0
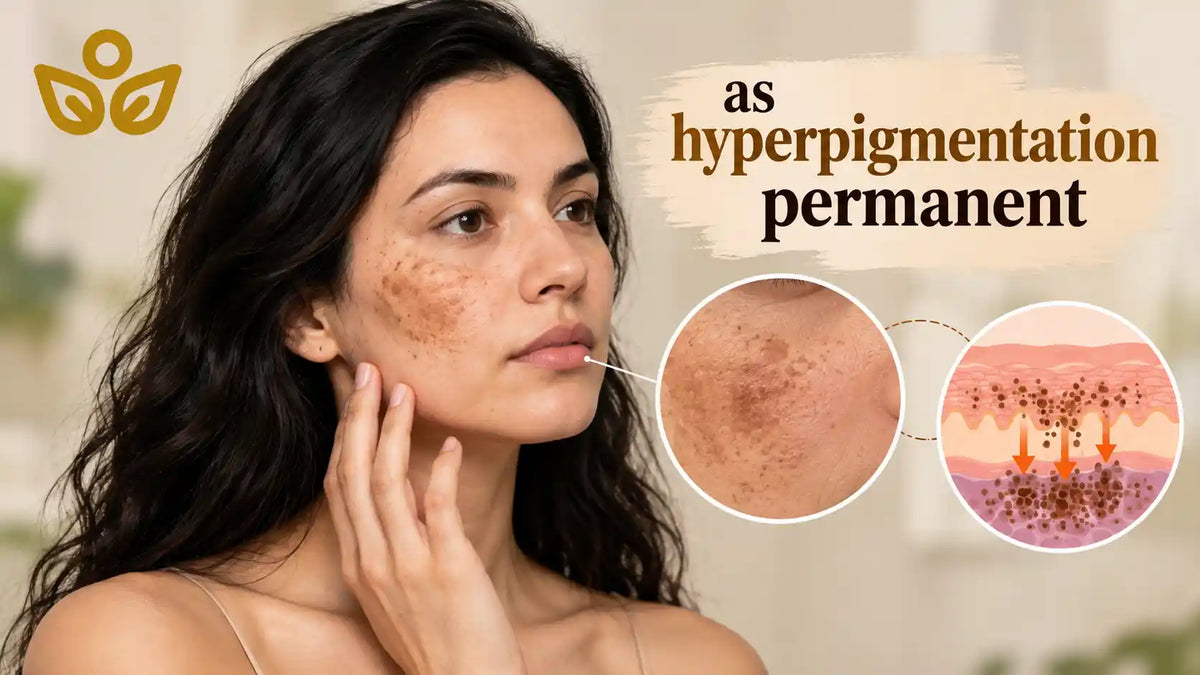
Hyperpigmentation can fade quickly at first, then stall when deeper pigment sits beyond effective topical reach. Epidermal pigment leaves through skin turnover, while dermal melanin can remain within the papillary dermis for years. Mixed hyperpigmentation often contains both compartments, which explains early improvement followed by a visible treatment plateau.
Melanocytes, keratinocytes, melanophages, inflammation, UV exposure, and pigment depth all influence how long dark marks remain visible. This guide explains why hyperpigmentation may appear permanent and why stronger topicals cannot always overcome a delivery limit. It also covers melasma, mixed pigmentation, Wood's lamp assessment, and the difference between permanence and limited topical reach. First, distinguish hyperpigmentation, melasma and sun spots before interpreting a mark's response.
Permanent Hyperpigmentation vs Pigment Beyond Topical Reach

Consumer content treats these as one thing. They are not, and the distinction changes what you do next. Permanent would mean the pigment cannot be removed by any means. Out of reach means a topical route cannot access it, which says nothing about other approaches or about very slow clearance over years.
Most of what gets called permanent hyperpigmentation is the second category. It is pigment in the dermis, where turnover does not carry it out and where topical delivery is poor.
That reframing matters because the two conclusions lead somewhere different. Permanent ends the conversation. Out of reach turns it into a question about what would reach it, which is a discussion to have with a clinician rather than a reason to stop. A different example of route dependent results appears in our oral versus topical minoxidil guide.
Epidermal vs Dermal Hyperpigmentation: Why Depth Matters

The epidermis is a conveyor. Cells form at the base, migrate upward, and shed. Pigment held in those cells is removed by that movement whether or not you do anything.
In epidermal hyperpigmentation, melanocytes are hyperactive, producing more melanin and transferring more of it into surrounding keratinocytes, with minimal involvement below. Suppress new production and the existing pigment leaves on schedule. For available formulations, browse skin brightening and hyperpigmentation products while keeping pigment depth in mind.
Dermal pigmentation follows a different route. When the basal layer is disrupted by inflammation, pigment escapes downward. Dyskeratotic keratinocytes carrying melanosomes are phagocytosed by melanophages, which migrate into the dermis and deposit melanin in the papillary dermis.
The dermis has no equivalent conveyor. Clearance depends on gradual removal rather than shedding, which is why timescales run into years and why some dermal pigment never fully clears.
Our findings from reader questions suggest most people treating pigmentation have never been told there are two compartments involved. Without that, a plateau reads as personal failure rather than as anatomy.
What a Treatment Plateau Means for Mixed Pigmentation
Most real world pigmentation is not purely one type. Mixed marks contain pigment at both depths, and that produces a characteristic response.
The epidermal fraction clears on its expected timeline. The dermal fraction barely moves. What you observe is improvement followed by a stop, at whatever level the remaining dermal component sits.
|
Feature |
Epidermal fraction |
Dermal fraction |
|
Clearance route |
Epidermal turnover |
Slow removal, no shedding route |
|
Typical appearance |
Light to mid brown, defined border |
Blue grey or slate, hazier border |
|
Topical reach |
Adequate |
Poor |
|
Response over 6 to 12 months |
Relatively good |
Minimal |
|
What it contributes to a mixed mark |
The part that improved |
The part that plateaued |
|
Under Wood's lamp |
Contrast sharpens |
Contrast does not sharpen |
Reading a plateau this way is more useful than reading it as failure. It tells you roughly what proportion of the mark was reachable, and it sets a realistic expectation for anything that continues on the same route.
Why Stronger Topicals May Not Reach Dermal Pigment

The instinct at a plateau is to escalate. Something stronger, higher, more frequent. That instinct misreads the constraint. Browse tretinoin creams by formulation, but do not treat strength alone as a solution to a plateau.
If the barrier is that the active cannot reach the papillary dermis in meaningful concentration, a more potent version of the same molecule delivered the same way does not solve it. It raises irritation without raising reach. Our tretinoin gel for oily skin guide discusses formulation choice, which is distinct from treating dermal pigment.
Irritation matters here beyond comfort. Inflammation is the mechanism that moved pigment downward in the first place. Escalating aggressively at a plateau risks producing exactly the compartment shift you are trying to reverse. If acne or wrinkles are also concerns, browse acne and wrinkle treatments with irritation risk in mind.
This is the argument for taking a plateau to a prescriber rather than solving it yourself. What is worth considering next depends on what is actually limiting the response, and that assessment needs someone who can examine the skin. Our tretinoin strength guide for acne, dark spots and wrinkles compares strengths by concern.
How Mixed Pigmentation Responds Over Time
Once you know two compartments are involved, the shape of a typical response stops being mysterious.
What the pattern usually looks like:
● little visible change in the first six to eight weeks
● steady improvement through months two to six as epidermal pigment clears
● slowing improvement through months six to twelve
● a plateau at the level set by the remaining dermal fraction
● no further meaningful change on the same approach beyond that
● gradual return if treatment stops and the driver is still active
● fresh pigment if inflammation or UV exposure resumes
The plateau point is informative. A mark that faded almost completely was mostly epidermal. One that improved slightly and stopped had a large dermal component from early on.
That is worth knowing before you start, because it sets an expectation you can actually meet, and it stops a reasonable result being read as a disappointment.
Why Melasma Often Needs Ongoing Management

Melasma illustrates the whole problem. It commonly involves both compartments, and its drivers, including UV, heat, visible light and hormonal influences, are not switched off by anything topical. The melasma and dark patches bundle groups routine components, though its products do not establish the mark's depth.
So even where the epidermal fraction responds well, the dermal fraction persists and the drivers continue. Suppression works while maintained and relapses when it stops.
That is not a failure of treatment. It is an accurate description of a chronic condition being controlled rather than eliminated, which is how clinicians frame it and how consumer content almost never does.
Judged against a cure, ongoing management reads as defeat. Judged against the untreated trajectory, holding ground is the outcome the treatment was capable of producing.
What to Do When Hyperpigmentation Stops Improving

Some things are worth checking before concluding a plateau is structural, because several ordinary explanations look identical. A hyperpigmentation and dark spots bundle is a routine option, not a substitute for depth assessment.
Whether sun protection has genuinely been consistent, since UV can add pigment at a rate comparable to what treatment removes. Whether irritation has been quietly limiting how often you apply anything. Whether the mark contains a textural component that was never pigment. And whether the assessment rests on photographs taken under fixed conditions or on impressions formed in a bathroom mirror.
If those are all clean and the plateau is real, that is the point to have depth assessed properly. A Wood's lamp examination distinguishes epidermal from dermal pigment quickly, and that result genuinely changes what is worth discussing next.
Take the photographs, the timeline, and an honest account of consistency. Decisions about changing, adding, or stopping belong with the prescriber assessing you, and they are much better decisions when made against a depth assessment rather than against frustration. Compare the listed ingredients in Melaglow Skin Brightening Cream 30g with your prescriber before adding a product. Do the same for Melaglow Prime Depigmenting Cream 20g if you are considering it.
Hyperpigmentation Plateau FAQs
Is a plateau the same as permanent?
No. A plateau on a topical route usually means the remaining pigment is not reachable by that route, which is a different statement from unremovable.
Can dermal pigment ever clear on its own?
It can reduce very slowly over years in some cases, and in others it is not fully clear. Slow is genuinely different from never, though neither is fast.
Should I switch to something stronger at a plateau?
Escalating potency does not address a delivery limit, and it raises irritation, which is the mechanism that moves pigment deeper. Raise it with your prescriber instead. Our tretinoin 0.05% versus 0.1% comparison may inform a strength discussion, not overcome a delivery limit.
Does stopping treatment undo the progress I made?
Progress on the epidermal fraction can be lost if the driver is still active, since new pigment production resumes. This is why maintenance is the usual framing.
How would depth actually be confirmed?
A Wood's lamp examination is the quick non-invasive method, and it distinguishes the two reasonably well. Where the picture is unclear, a biopsy can settle it.
Why does my mark look greyish rather than brown now?
Colour shifting toward grey or slate can reflect a greater dermal contribution. It is worth having examined rather than treated more aggressively. A raised spot may need a different diagnosis; our flat warts and tretinoin guide covers one example.
Is there any point continuing once I have plateaued?
Often yes, because stopping usually means losing ground rather than holding it. That judgement belongs with whoever is overseeing your treatment.
Conclusion
A plateau is not a verdict on whether pigmentation is permanent. Epidermal pigment leaves with turnover, dermal pigment has no such exit, and most real marks contain both, which produces improvement followed by a stop at whatever level the deeper fraction sits. Escalating potency does not fix a delivery limit and risks the inflammation that sends pigment downward to begin with. Sun protection remains the condition for any of it to show. Take a real plateau, dated photographs and an honest account of consistency to your prescriber, and ask specifically about depth. Explore more active treatment guides on tretinoins.co.za for routine support. Explore all products only after the diagnosis and treatment goal are clear.